



Growth planning starts with a boundary, and for most health plans, that's their service-area map: where they’re licensed, where their network sits, and where enrollment gets counted.
But that map has blind spots. It can't tell you where an employer's workers actually live, or which providers they turn to for care. Those patterns decide whether members can reach your network, and whether they stay in it.
Your service area tells you where you can sell. Your market tells you whether members can reach you and stay.
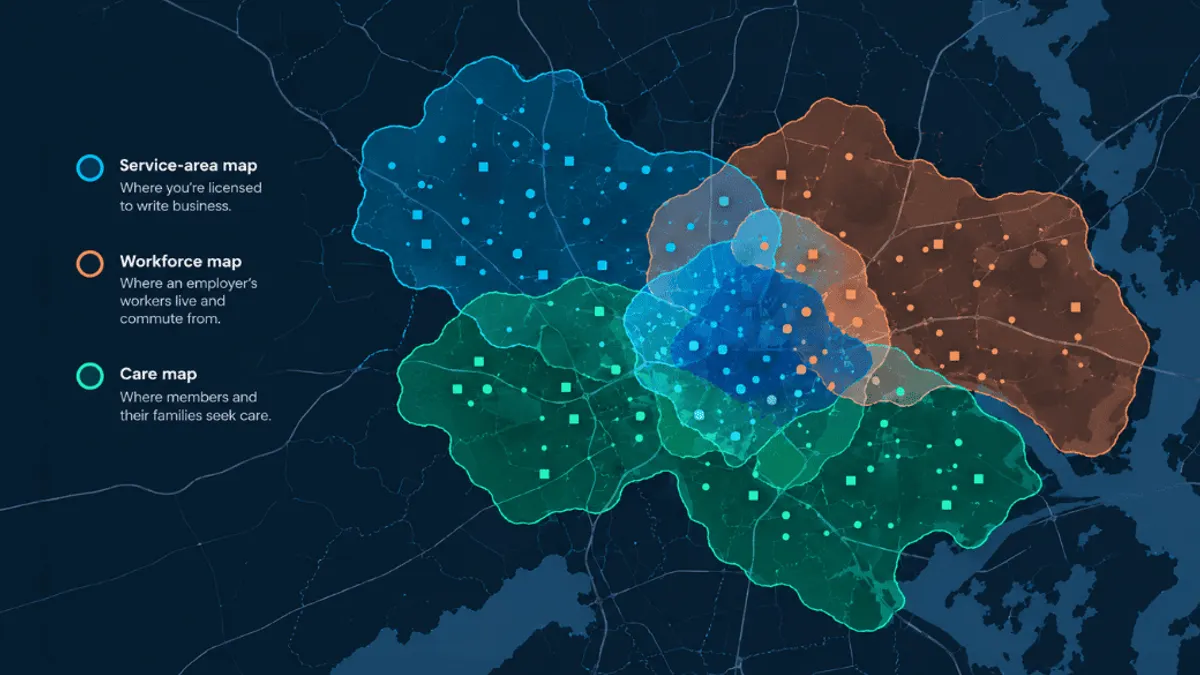
The fix is to read three maps together, not one: where you're licensed, where the workforce lives, and where members seek care.
Three maps, one real market
Service-area maps still matter for licensing, contracting, and enrollment. But they only show where you can operate. To see the real market, read three maps together:
- The service-area map shows where you’re licensed to write business: the footprint you already plan around.
- The workforce map shows where an employer’s workers live and commute from. A company may sit in one county but draw its workforce from three, and demand, providers, and competitors follow the workforce, not the headquarters.
- The care map shows where those members and their families seek care: the providers they rely on and the access that keeps them enrolled.
Where the three maps overlap? Your real market and opportunity.
Where the three maps diverge? These are the gaps in network reach, product fit, or account strategy.
The cost of backing the wrong market
A market misjudged from the service area alone is an expensive mistake, and an easy one to make. Employer coverage is the largest source of health coverage in the country: KFF's 2025 Employer Health Benefits Survey puts the number at 154 million people under 65, with family coverage averaging $26,993 per year, of which workers pay $6,850 and employers cover the rest. For the plans competing to win that business, every employer account is an expensive bet, and the sales, network, and product budget behind it is finite.
If your budget is allocated to a market drawn without the three-map overlap, you risk building a network where there isn’t a workforce and chasing accounts your members can't reach. And members who can't conveniently access care are more likely to leave. Since retention typically costs less than acquisition, a network that misses the workforce drives up your acquisition costs.
The reality is this: A national plan can absorb those mistakes across a big book. A regional or mid-market plan can't: one bad market bet moves the whole book.
Four questions to answer before you commit to a market
Before you consider a market or pursue an employer, look past the headquarters and ask:
- Is this boundary drawn from market behavior, or just contract structure?
- Where do the employer and its workforce actually live and commute?
- Does your network reach where members live and seek care?
- Who already competes there, and what would you need to change to win?
Your answer to each question helps you decide your next move: pursue the account, protect your share, strengthen the network, or keep watching. It doesn’t replace the service-area map; it gives you the context to use it better.
Health plans that account for employers, workers, providers, and competitors make sharper calls about where to grow and where to hold back. Bottom line? The goal is a map that matches the market.
Data Axle for Healthcare provides regional and mid-market health plans with a unified view of their market. Built on SignalFuse, it brings together employer, member, geographic, competitive, and healthcare data so teams can see where opportunity is strongest, which accounts to prioritize, and where risk is emerging. Learn more here.








